

OpenEvidence

- 146.00 Reviews
- 4.9
- Downloads
- 500,000+

Our take on OpenEvidence from Appgk
OpenEvidence is a medical app from OpenEvidence that I would describe as a focused point-of-care reference rather than a general health companion. Its purpose is to help clinicians look for accurate answers while working, and that distinction matters from the first screen: this is aimed at professional medical use, not at replacing a doctor’s appointment or helping a casual user interpret every symptom at home. I found the idea most useful when a question needed a quick, structured starting point without opening several unrelated resources.
The app is free, carries an Everyone age rating, and requires an NPI for access. That requirement immediately tells you who it is built for. If you are a clinician with the necessary identification, it can fit into a busy workflow; if you are a patient, student without the required access, or family member searching for reassurance, it is probably not the right download. The Android release has reached over 500 thousand installs and holds a 4.9 average from around 4.5 thousand ratings, which suggests strong interest and a notably positive reception, although those figures alone cannot tell you whether it matches your specialty or daily routine.
How OpenEvidence feels to use in real clinical situations
Readable answers are more important than visual decoration
What stood out to me is the value of getting to a medical answer with less visual noise than I usually associate with broad web searches. A clinician who is already thinking through a case does not need a page crowded with unrelated headlines, advertisements, or consumer-oriented explanations. The appeal here is the possibility of keeping the question and the resulting information in the same professional context.
That can make a difference during a short pause between patients. Imagine reviewing a case and wanting to check a treatment consideration, a diagnostic distinction, or the clinical reasoning behind a decision. Instead of opening several browser tabs and sorting through pages written for different audiences, I would use OpenEvidence as a first pass: phrase the question clearly, inspect the answer, and then decide whether the issue needs deeper checking in a guideline, textbook, journal, or local protocol.
Best Parts of OpenEvidence
Things to Keep in Mind About OpenEvidence
The best way to improve readability is to write the question as a clinical task rather than a vague topic. “What is condition X?” is broad and may produce information that is less useful at the bedside. A question that identifies the patient context, the decision being considered, and the uncertainty you want to resolve is more likely to support a practical review. I would still read the response carefully rather than treating the first sentence as a final recommendation.
For users with dyslexia, attention difficulties, or limited time, focused answers can reduce the burden of scanning. That is a meaningful accessibility advantage even without claiming that the app provides specialized accessibility tools. The benefit comes from reducing the amount of irrelevant material a person must process. On the other hand, concise presentation can also become a weakness if an answer feels too compressed. Medical decisions often depend on exceptions, contraindications, patient preferences, and local standards, so readability should never be confused with completeness.
News and Features Related to OpenEvidence

News
YouTube Turns a Quick Video Check Into an Hour of Watching

News
BeautyPlus Makes Portrait Retouching Feel Like Your Own
News
TikTok’s Effortless Feed Makes Every Swipe Count—and Every Mistake Harder to Undo
Navigation works best when the question is already clear
I see OpenEvidence as an app that rewards preparation. If I know exactly what I need to clarify, the interaction feels direct. If I am still defining the problem, it is less likely to replace a full reference workflow. That is not a defect unique to this product; it is the trade-off of an answer-oriented tool. Search engines are better for discovering a broad range of sources, while a traditional medical database is often better when I need to trace literature, compare documents, or build a detailed evidence trail.
A practical habit is to separate quick orientation from verification. I would first use the app to organize the issue and identify the main considerations. Then I would open the source or reference system required by my workplace when the decision is high risk, unusual, or likely to be audited. This two-step approach protects against overconfidence and makes the app more useful: it becomes a fast reasoning aid, not the only authority in the room.
Don't want to read the full review?
The current version is 2.9.25, and the app runs on Android 7.0 or later. That broad operating-system reach is helpful for people using older phones, clinic-owned devices, or hardware that is not replaced frequently. It also means the app can be considered in environments where the newest phone is not guaranteed. Still, an older device may have its own performance, display, or battery limitations, so the experience will not necessarily feel identical across every handset.
Motor and sensory needs deserve a realistic assessment
From an inclusive-use perspective, a medical reference app has to work during imperfect moments: standing at a workstation, holding a phone with one hand, moving between rooms, or dealing with glare and background noise. OpenEvidence’s usefulness in those situations depends heavily on the device and the user’s setup. A larger display, increased system text size, and a quiet review moment can make reading much easier, while a small screen or rushed one-handed interaction can make even a well-organized answer tiring.
Screenshots
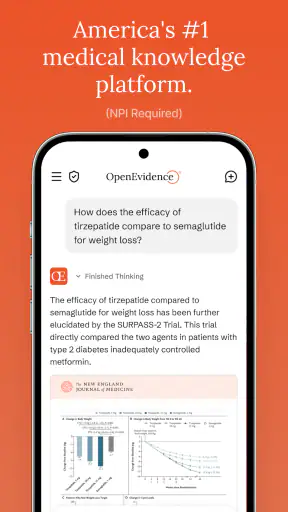

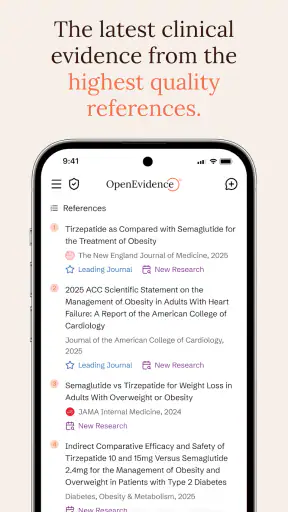
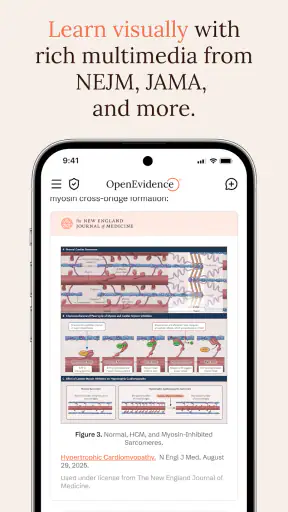
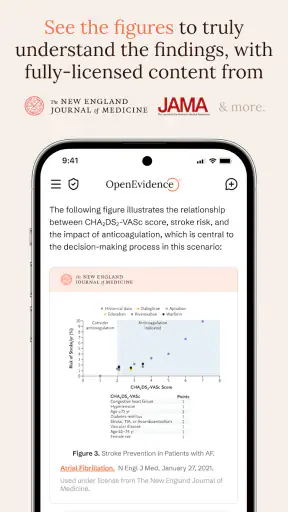
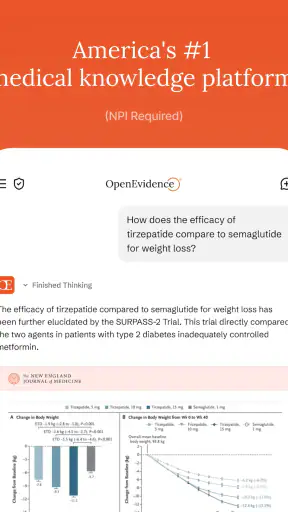

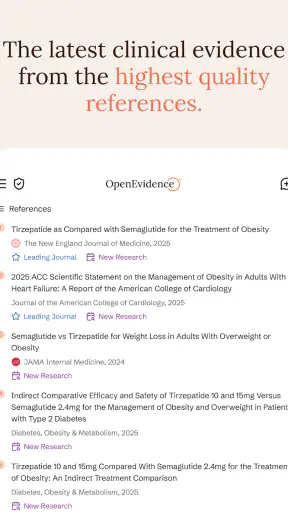
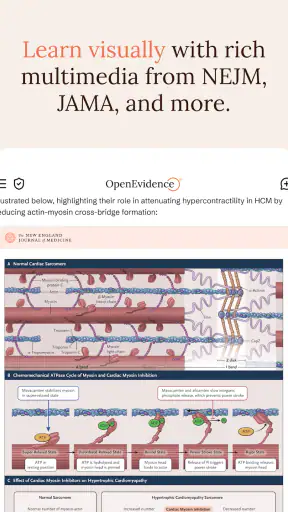
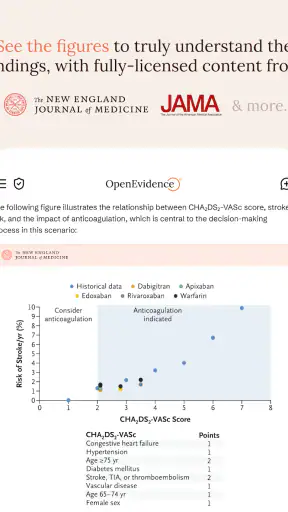
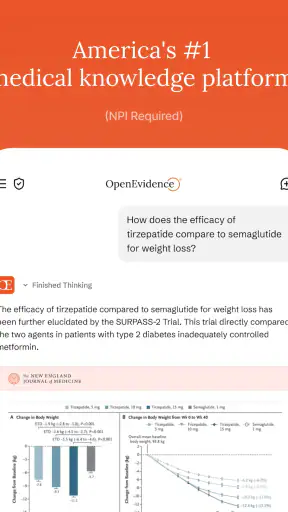

I would not recommend judging the app only in a calm home setting. Try it in the environment where you actually intend to use it. Check whether the text remains comfortable when the phone is held at arm’s length, whether the question can be entered without awkward repeated taps, and whether the answer is easy to follow when attention is divided. These are simple tests, but they reveal more about practical accessibility than a feature checklist.
For clinicians with low vision, the phone’s own accessibility settings may be especially important. Larger text can improve comfort, but it can also change how much information fits on screen, requiring more scrolling. High contrast or display adjustments may help some people, while others may find them visually harsh. Because individual needs vary, I would treat the operating system’s settings as part of the overall experience rather than assuming the app alone solves every reading challenge.
Users with motor impairments may prefer to prepare questions before a busy session, use a stable surface, or rely on their device’s standard input assistance where available. The key trade-off is speed versus precision: a short question is quicker to enter, but a carefully worded question may prevent extra back-and-forth and reduce the physical effort of correcting an unclear request. That is one of the less obvious ways to make the app more accessible in practice—improve the first input instead of repeatedly editing the result.
For sensory-sensitive users, the focused medical context may be preferable to a crowded web page full of animated elements and competing content. Yet clinical settings can be noisy, bright, and stressful. I would use the app as a quiet reading tool rather than assuming it is suitable for listening while multitasking. When the information affects patient care, visual confirmation and deliberate reading are safer than trying to absorb an answer while walking or speaking with someone else.
Situational access: where the app earns its place
The strongest everyday scenario is the short clinical pause. I can picture a practitioner finishing an appointment, identifying one unresolved question, and using the app before the next task begins. The value is not that it eliminates professional judgment; it is that it can shorten the distance between uncertainty and a structured review. That makes it more relevant to point-of-care work than a general medical encyclopedia designed for leisurely browsing.
It may also help when a clinician wants to prepare for a conversation. Before explaining a condition or discussing options, a quick review can help organize the topics that deserve attention. I would still adapt the explanation to the patient’s language and needs rather than showing an app-generated answer as if it were patient education. Professional wording can be accurate yet unsuitable for someone who has no medical background.
Another useful workflow is comparing the app’s answer with an established resource when the case is complicated. If both point toward the same considerations, the app has saved time. If they differ, that difference is a signal to slow down, inspect the evidence, and consider whether the question was too broad or missing important context. In my view, disagreement is not automatically a failure; it can expose where a quick answer needs a more careful review.
Access is less straightforward for people who work in settings with restricted phones, limited connectivity, or strict rules about entering clinical information into external services. I would avoid typing identifiable patient details and would follow workplace privacy and security procedures before using any medical question tool. The safest habit is to keep questions general enough to protect confidentiality while retaining the clinical facts needed for a useful answer.
The NPI requirement is another situational boundary. It supports the app’s professional focus, but it also excludes people who might want to explore medical topics for education. A nursing student, researcher, caregiver, or patient may find that a library database, official health service, or textbook is a better fit. This is not an app I would recommend simply because it is free; the access condition and intended audience matter more than the price.
Where OpenEvidence remains limited
The biggest limitation is the risk of treating an answer engine as a substitute for clinical responsibility. Even a highly rated medical app cannot know every detail of a patient, every local policy, or every change in a person’s condition. A confident-sounding response may still need confirmation. I would be particularly cautious with urgent decisions, rare presentations, medication safety, and situations where a small missing detail could change the recommended path.
There is also a difference between finding an answer and understanding its evidence. A traditional medical database may be slower but better when I need original studies, publication context, search filters, citation management, or a documented research trail. A guideline portal may be preferable when a hospital requires a specific local standard. OpenEvidence is more attractive when speed and synthesis are the immediate priorities; it is less suitable when the task is formal literature review or exhaustive documentation.
Another barrier is the learning curve around question design. Someone expecting a simple keyword search may be disappointed if the result does not match the exact issue they had in mind. The solution is not to type longer questions indiscriminately. I would name the clinical setting, identify the decision, and state what comparison or uncertainty matters. Then I would read the answer for scope: does it address the actual patient situation, or merely a nearby topic?
People with limited digital confidence may also need time to develop that habit. The interface can be focused and still require judgment. A clean presentation does not automatically explain how to challenge an answer, spot a missing assumption, or decide when another source is necessary. For team use, a short local guide on safe phrasing and verification would make more difference than simply telling staff to download the app.
Accessibility has similar limits. The app can be part of an accessible workflow, especially when paired with system-level text and display settings, but I would not assume that every user’s needs are covered. People who depend on a particular assistive setup should test the current release directly on their own device. Those who cannot comfortably type, read a phone screen, or work in a noisy clinical environment may prefer a reference system that fits their existing tools better.
Who should use it, and who should choose something else?
I would recommend OpenEvidence to an eligible medical professional who wants a quick way to frame clinical questions during the workday. It is especially appealing if you dislike sorting through consumer search results and want a more focused starting point. The free price removes one common barrier to trying it, while the broad Android compatibility makes it practical for a range of devices.
I would not recommend it as a patient-facing diagnostic app, a replacement for emergency care, or the only reference used for consequential decisions. Patients should speak with an appropriate healthcare professional, and clinicians should use local protocols and trusted primary resources when the situation demands detailed verification. Students and researchers may also prefer tools built around textbooks, journal discovery, citations, and systematic searching rather than rapid point-of-care answers.
My most useful tip is to create a personal boundary for the app: use it for orientation, targeted clarification, and preparation, then escalate to a guideline or primary source whenever the decision is high stakes. A second is to remove patient-identifying information from every question. A third is to test readability with the accessibility settings you already depend on, because the same answer can feel manageable on one screen and exhausting on another.
OpenEvidence was released on October 1, 2024, and its strong reception gives it a credible place among modern medical reference tools. Still, popularity should not decide whether it belongs in your workflow. The more important question is whether its answer-focused design helps you think clearly without encouraging shortcuts.
My inclusive verdict is positive but measured. OpenEvidence is most valuable when it reduces search friction while leaving clinical judgment firmly with the professional. Its focused purpose can support readability, quick access, and a calmer information workflow, particularly for eligible users who adapt their device and question style to their needs. It is not a universal accessibility solution, and it should not replace detailed evidence sources or local clinical guidance. For the right user, however, this free medical app is a sensible first stop when a focused question appears in the middle of a busy day.
If I were recommending it to a friend in healthcare, I would say: try it with low-risk questions, learn how it handles your wording, adjust your phone for comfortable reading, and keep a verification habit from the beginning. Used that way, OpenEvidence feels less like a shortcut and more like a practical companion for the first stage of clinical reasoning.
OpenEvidence FAQ
What is OpenEvidence and who is it designed for?
OpenEvidence is an AI-powered medical information platform designed primarily for healthcare professionals, including physicians, nurses, and other clinical users. It is intended to help users find concise, evidence-based answers to medical questions by referencing current literature and clinical sources. It is not a general-purpose chatbot or a substitute for professional education, clinical judgment, institutional protocols, or consultation with qualified specialists.
Can OpenEvidence be used to diagnose patients or make treatment decisions?
OpenEvidence may support clinical research and point-of-care information gathering, but it should not be used as the sole basis for diagnosing a patient, prescribing medication, or selecting a treatment. AI-generated answers can contain mistakes, omissions, or outdated interpretations. Before applying any information, users should verify the cited evidence, consider the individual patient’s history and condition, and follow local guidelines, professional standards, and institutional policies.
Does OpenEvidence provide sources for its medical answers?
One of OpenEvidence’s main purposes is to make medical information easier to review by connecting answers with supporting evidence and clinical references. However, users should still inspect the cited material rather than relying only on the summary generated by the app. The availability, depth, and presentation of references may vary depending on the question, topic, account type, and platform version, so important decisions require independent verification.
Is patient information safe to enter into OpenEvidence?
Users should be very careful when entering clinical information into any AI application. Avoid submitting names, identification numbers, photographs, contact details, or other personally identifiable health information unless the service, your organization, and applicable regulations clearly permit it. Review OpenEvidence’s current privacy policy, data-handling terms, and account settings before use. When possible, describe cases in a de-identified way and follow your workplace’s security requirements.
Is OpenEvidence free, and what do I need before downloading it?
Access to OpenEvidence may depend on eligibility, region, professional status, account registration, or changes to the provider’s access policy. Some users may receive access without a traditional subscription, while certain features or services can require verification or an approved account. Before downloading, check the official App Store or Google Play listing for supported devices, current requirements, privacy details, and any limitations that apply to your location.











